
Freud’s Oral Stage: Oral Receptive vs Oral Aggressive Types
Picture two classmates in your 9 a.m. lecture. One has chewed through two pen caps before the professor finishes the first slide. The other has a sarcastic comment ready for every point on the screen. Sigmund Freud would say both habits could trace back to the same starting point: Freud’s oral stage, the period when a baby’s whole world revolves around feeding. What happens there, he argued, can tilt a person toward one of two very different personality styles. The more interesting question is how well that claim has held up.
Key Takeaways
- The oral stage revolves around feeding, but its defining conflict is not hunger. It is the first time a baby has to cope with losing something comforting.
- Too much comfort and too little comfort were thought to produce opposite adult personalities: one that leans on others and one that bites back.
- Several labels students memorize for this stage were not coined by Freud, and two of the most common ones describe exactly the same type.
- Researchers did find personality clusters that resemble Freud’s descriptions. The part they could not confirm is the explanation for where those traits come from.
- One term that shows up constantly on quizzes and in search bars, “oral retentive,” does not actually belong to this stage.
How the Oral Stage Fits Freud’s Theory
Freud believed personality develops through a series of childhood stages, each centered on a body zone where the id’s pleasure-seeking energy concentrates. Among Freud’s five psychosexual stages, the oral stage comes first, running from birth to roughly 12 to 18 months. Sources differ slightly on the exact cutoff.
You will also see it called the oral phase. Translations and textbooks use “oral phase” and “oral stage” interchangeably, so treat them as the same concept.
During this window, the mouth is far more than a tool for eating. Comfort, pleasure, connection, and early exploration all pass through sucking and feeding (Freud, 1905).
Freud also argued that the way feeding is handled matters psychologically. An infant who is fed warmly and reliably starts to sense that the world is responsive. An infant whose feeding is inconsistent or frustrating learns the opposite. Those early experiences, in his view, become templates for how a person handles dependency later in life.
Why the Mouth Matters So Much in Infancy
Biology reinforces the mouth’s importance from day one. The rooting reflex turns a newborn toward a touch on the cheek, and the sucking reflex lets them draw milk. Neither has to be learned.
What caught Freud’s attention was what happens beyond survival. Babies suck on thumbs, pacifiers, and toys when they are not hungry at all. This non-nutritive sucking soothes distress, which makes it one of the earliest forms of self-regulation.
The mouth is also the infant’s first research instrument. Before their hands are coordinated, babies explore objects by mouthing them, testing texture, hardness, and temperature.
Because feeding happens many times a day, Freud saw the feeding relationship as a prototype for later relationships. The breast or bottle comes bundled with warmth, closeness, and eye contact. That bundling of physical satisfaction with emotional connection is what gives the oral zone its lasting psychological weight in his theory.
The Caregiver’s Role During the Oral Stage
Freud placed the caregiver at the center of this stage. Prompt, warm responses to hunger do more than meet nutritional needs. They set the emotional tone of the infant’s first experience of the world.
Erik Erikson made a similar point with trust vs. mistrust, his first psychosocial stage, which covers the same age window. The differences between Erikson and Freud are real, but on this point the two theorists largely agree.
Later, attachment theory provided empirical support for the general principle. Sensitive, responsive caregiving is associated with secure attachment (Bowlby, 1969; Ainsworth et al., 1978).
Harlow’s cloth and wire mother studies pointed in a similar direction. Infant monkeys spent their time clinging to the soft surrogate rather than the wire one that dispensed milk. Comfort, not just food, mattered.
Weaning: The Infant’s First Experience of Loss
The central conflict of Freud’s oral stage is weaning, the gradual shift from breast or bottle to other foods. Practically, it is a change in feeding. Psychoanalytically, it is the infant’s first major loss.
Freud described early infancy as a state of primary narcissism, where needs seem to be met almost automatically and the baby barely separates self from caregiver. Weaning disrupts that. Satisfaction now requires waiting.
This is where ego development begins. The infant starts shifting from the pleasure principle, which demands immediate satisfaction, toward tolerating delay and frustration (Freud, 1917).
Timing and style matter in this account. Abrupt or premature weaning was thought to create excessive anxiety. Delayed or overly indulgent weaning was thought to block the development of frustration tolerance. Gradual weaning that follows the child’s readiness, with continued warmth, was Freud’s picture of a healthy passage through the stage. The goal was never to avoid frustration completely. A manageable dose of it was exactly what pushed the ego to grow.
What Is Oral Fixation?
In Freudian terms, a fixation happens when part of a person’s libidinal energy stays anchored at an earlier stage instead of moving forward. Oral fixation can be triggered by either extreme: too much frustration or too much gratification during the first year or so of life.
Either way, the person keeps seeking oral-stage forms of comfort into adulthood. Freud’s followers described two distinct patterns, each linked to a different early experience.
These are not clinical diagnoses. Most people who recognize a trait or two from the descriptions below do not have a full fixation in Freud’s sense. They simply show tendencies that a Freudian would trace back to this window (Kline & Storey, 1977).
Oral Receptive, Oral Passive, Oral Incorporative: Same Type, Different Names
Here is a detail many summaries skip. Freud described the oral stage as a single period. The split into two sub-phases came from his colleague Karl Abraham in 1924.
Abraham distinguished an early sucking phase in the first months of life from a later biting phase that begins with teething. He called the later phase oral sadistic, because biting introduces aggression toward the very thing the infant loves (Abraham, 1924/1927).
Textbooks then attached personality types to each sub-phase, and the labels multiplied. The early, sucking-based type appears as oral receptive, oral passive, or oral incorporative. All three names describe the same pattern. The later, biting-based type appears as oral aggressive or oral sadistic.
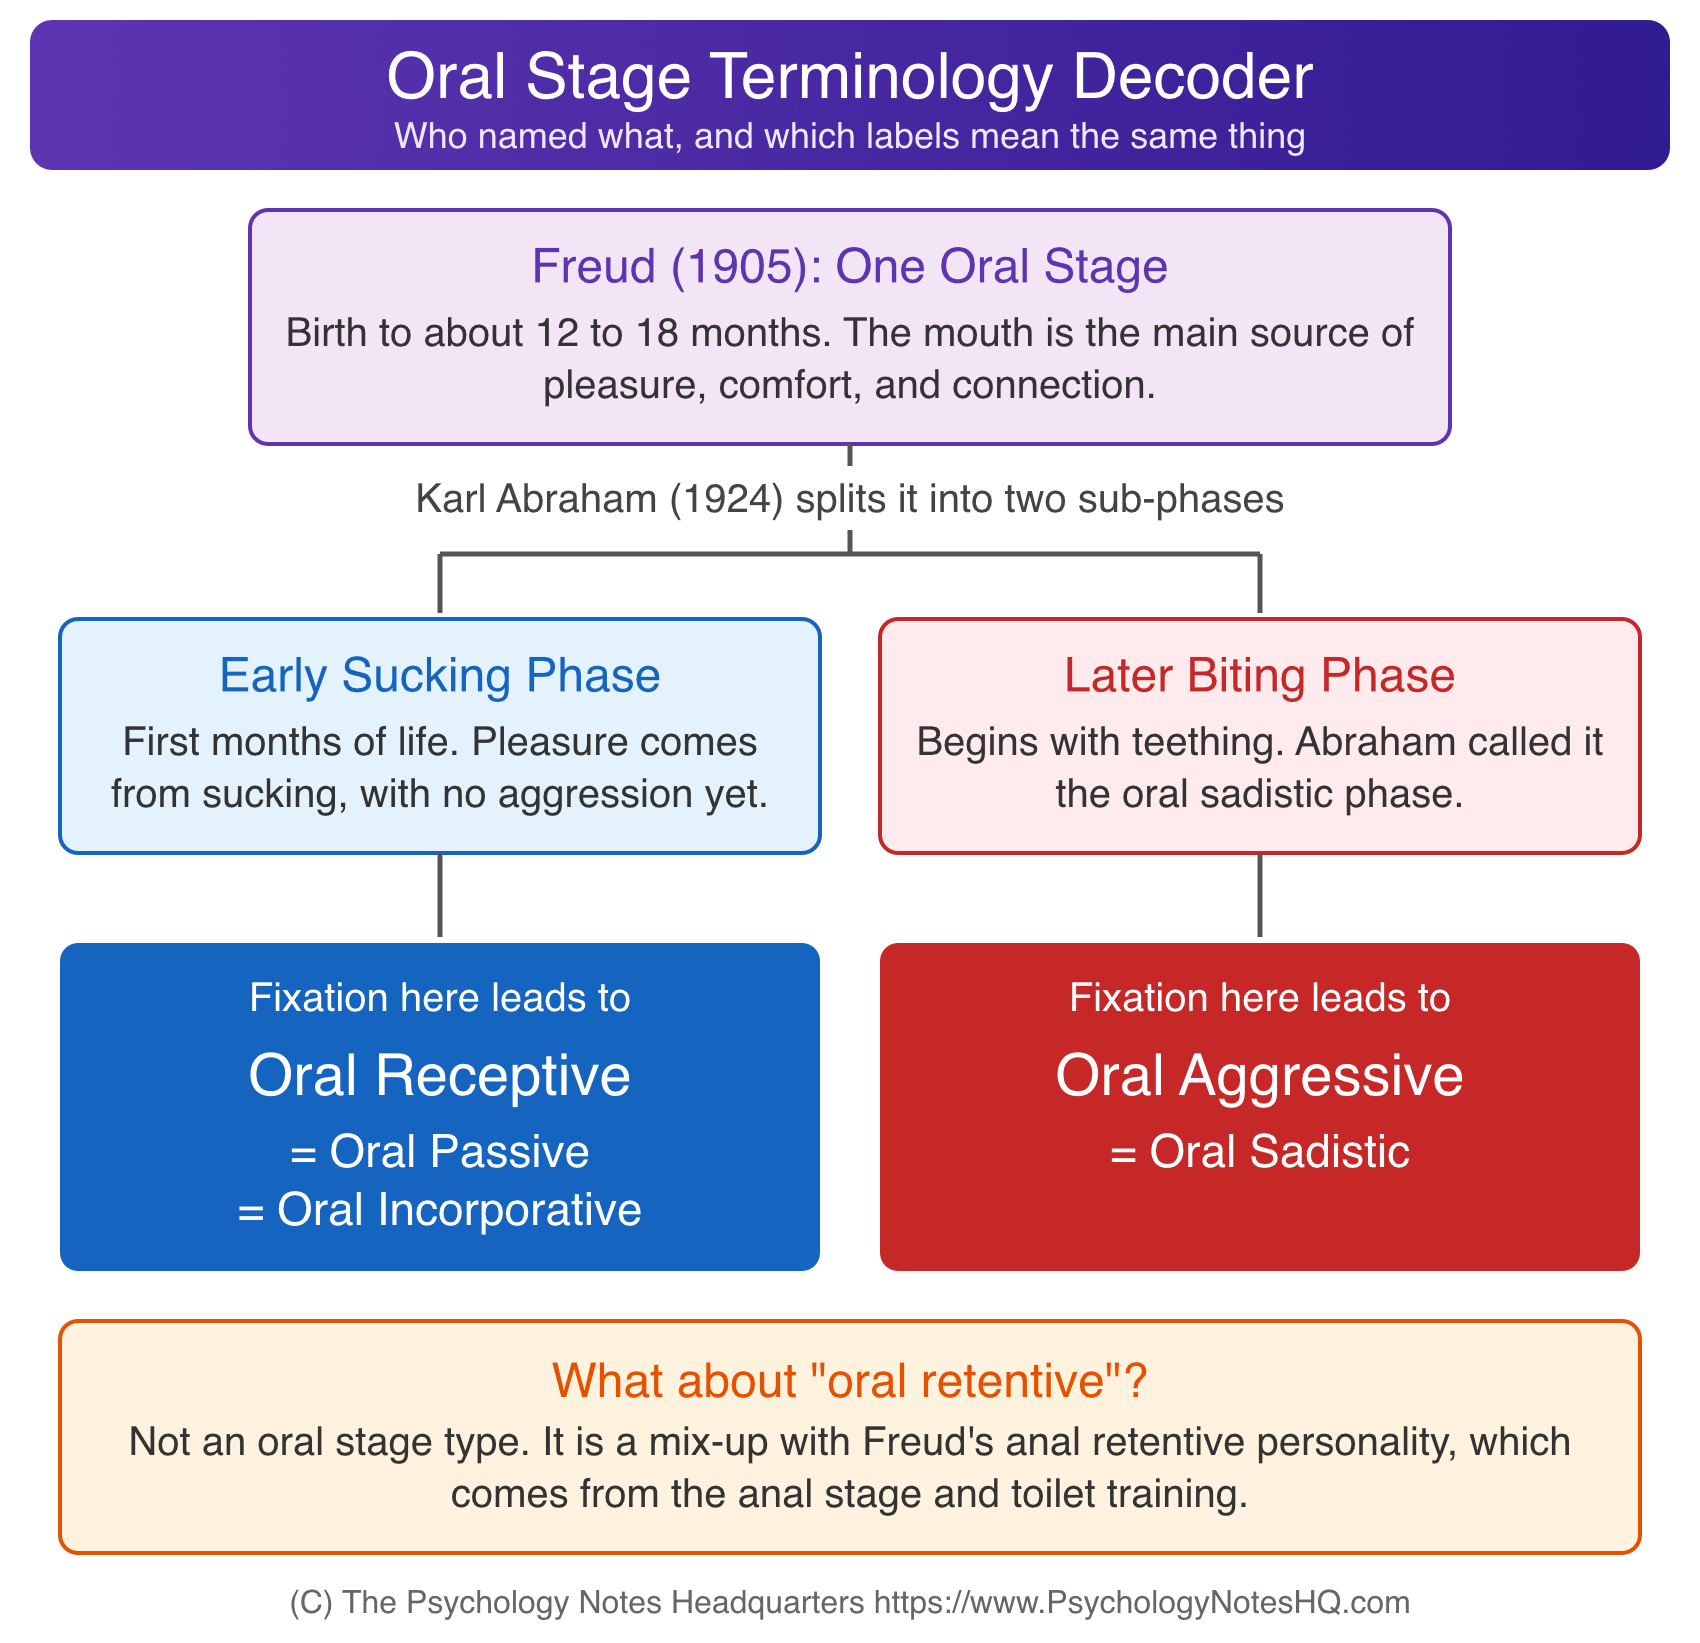
What about “oral retentive”? It is not a Freudian type at all. Students usually blend it with the anal retentive personality from the anal stage, which concerns control and toilet training rather than feeding.
Oral Receptive Personality: The Dependent Type
The oral receptive pattern is usually linked to overindulgence. When an infant’s oral needs are met instantly and weaning is long delayed, Freudian theory holds that the child never fully learns to tolerate frustration or function independently.
Dependency is the defining adult trait. Oral receptive individuals look to others for emotional and practical support, often without realizing how much they rely on it. Making decisions alone feels uncomfortable.
Gullibility often comes with it. Just as the infant accepted whatever was offered, the oral receptive adult tends to swallow claims without much scrutiny.
There is also a characteristic optimism, a confidence that needs will be met because they always were. It can be charming, but it often comes without much planning for setbacks.
The most visible signs are oral habits: smoking, stress eating, nail-biting, constant snacking, and gum chewing. In Freudian terms, each one recreates the soothing quality of being fed (Freud, 1905).
Oral Aggressive Personality: The Biting Type
If the receptive type comes from too much, the oral aggressive personality comes from too little. Abrupt weaning or chronically frustrating feeding was thought to push the infant toward hostility instead of dependency. In Abraham’s framework, this pattern belongs to the later biting phase, when teeth give frustration a new outlet.
Adults with this pattern tend to “bite” with words. Sarcasm, cutting remarks, and blunt criticism are the adult versions of infant biting.
Pessimism is a core feature, the mirror image of the receptive type’s optimism. Having experienced early deprivation, these individuals come to expect disappointment and can be argumentative and suspicious of other people’s motives.
Envy runs through the type as well. Abraham tied events in the oral period to adult traits ranging from lasting optimism to a sarcastic, envious streak (Abraham, 1924/1927). For the oral aggressive adult, someone else’s success can feel like a personal loss.
Signs of Oral Fixation in Adults at a Glance
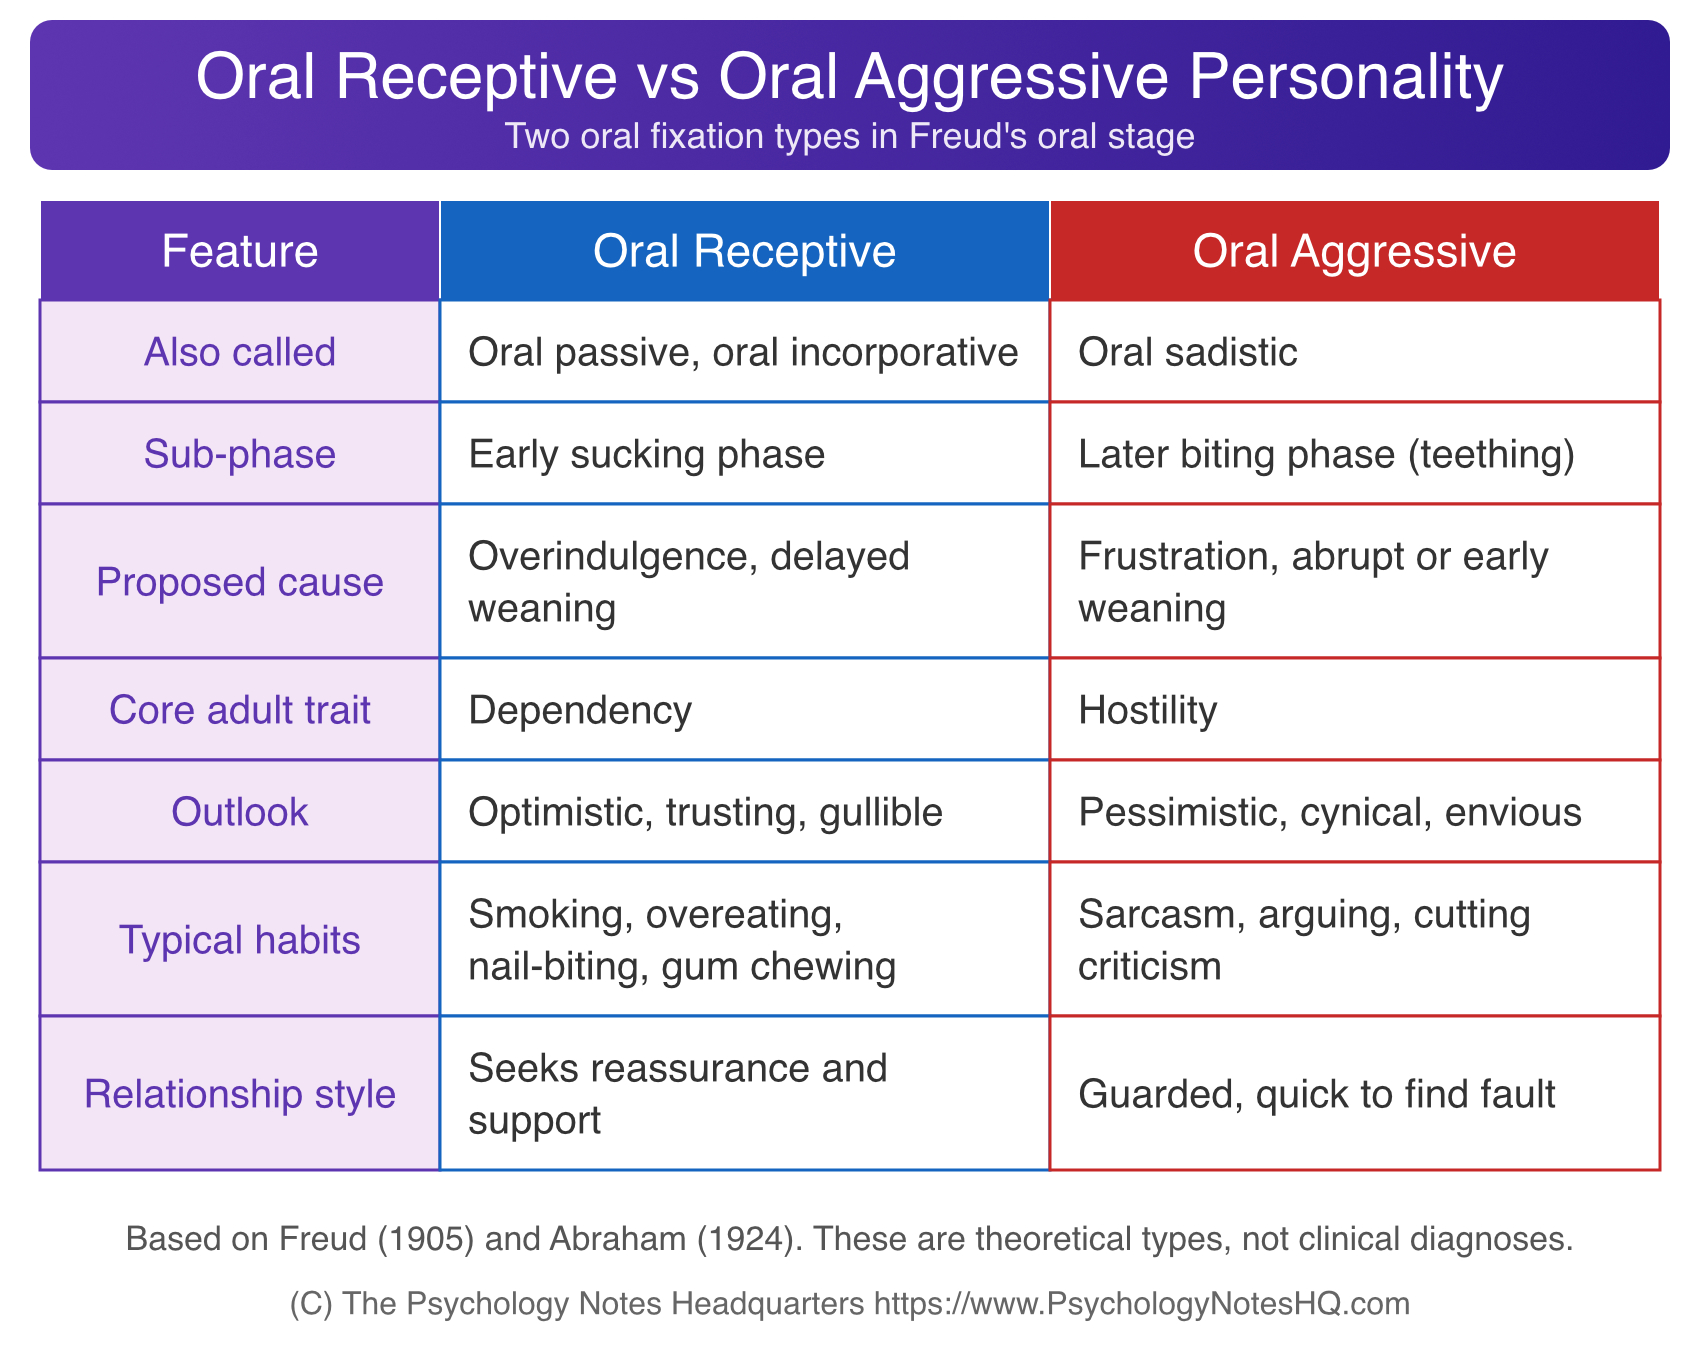
The table below sums up how Freudian theory describes the two patterns side by side.
| Feature | Oral Receptive (Passive, Incorporative) | Oral Aggressive (Sadistic) |
|---|---|---|
| Proposed cause | Overindulgence, delayed weaning | Frustration, abrupt or early weaning |
| Sub-phase | Early sucking phase | Later biting phase (teething) |
| Core adult trait | Dependency | Hostility |
| Outlook | Optimistic, trusting, gullible | Pessimistic, cynical, envious |
| Typical habits | Smoking, overeating, nail-biting, gum chewing | Sarcasm, arguing, cutting criticism |
| Relationship style | Seeks reassurance and support | Guarded and quick to find fault |
Keep one caution in mind. Habits like snacking or nail-biting have many explanations, including stress, boredom, and learned routines. Signs of oral fixation in adults are a Freudian interpretation of behavior, not a diagnostic checklist.
What Research Actually Found
Freud’s ideas about oral fixation have been tested more directly than most students realize, and the results split in an interesting way.
Kline and Storey (1977) built two questionnaires measuring oral optimism and oral pessimism, refined them on 457 participants, and cross-validated them on another 100. A factor analysis supported the existence of two personality clusters that resemble the oral types psychoanalysts described.
Then they tested where those traits come from. Across eight hypotheses drawn from psychoanalytic theory and 615 students, three results fit the theory, but only one (a link between oral pessimism and smoking) was at all conclusive. Five went against it. Kline and Storey (1980) concluded that the psychoanalytic account of how the oral character develops should be rejected.
Bornstein’s (1992) review of dependency research reached a similar verdict. Evidence that dependent traits grow out of infant feeding and weaning was weak. Instead, dependency was most consistently linked to overprotective and authoritarian parenting, two patterns that overlap with Baumrind’s parenting styles.
The short version: the trait clusters seem real, but the weaning explanation does not hold up. For students, that is a useful lesson in separating a theory’s descriptions from its causal claims, because the two can succeed or fail independently.
Cultural and Methodological Limits
Freud built his theory from adult patients’ memories in therapy, not from observing infants. That makes the oral stage’s causal claims hard to test directly.
Early studies tried to fill the gap by asking mothers to recall how they fed and weaned their children years earlier. Bornstein (1992) pointed out that such retrospective reports may not be accurate.
There is also a chicken-and-egg issue. Even when an adult with dependent traits was weaned late, the late weaning and the later dependency could both reflect a broader parenting style rather than one causing the other.
Culture adds another problem. Weaning age and feeding practices vary widely around the world. What looks like overindulgence in one setting is standard practice in another, which makes Freud’s universal claims about this stage difficult to defend.
Common Exam Mix-Ups About the Oral Stage
A few distinctions trip up psychology students again and again.
Oral receptive, oral passive, and oral incorporative are one type with three names. Oral aggressive and oral sadistic are the other type.
Fixation can come from either extreme. Students often remember frustration as the only cause, but overindulgence counts too.
The sucking and biting split belongs to Karl Abraham, not Freud. If an exam asks who divided the oral stage into two sub-phases, the answer is Abraham.
Scenario questions follow the theory’s logic. An infant fed on a rigid schedule that ignores hunger cues experiences frustration, which points toward the oral aggressive and pessimistic end of the spectrum.
Finally, do not mix Freud’s stage with Erikson’s. Both cover infancy, but Erikson’s trust vs. mistrust focuses on social relationships rather than an erogenous zone. Virtues are also Erikson’s idea. Hope belongs to his first stage, while Freud’s stages produce fixations, not virtues.
Why Freud’s Oral Stage Still Matters
The specific mechanics of Freud’s oral stage have not survived scientific testing well. Its broader message has.
Freud treated the first year of life as psychologically important, not just physically important, at a time when that was a bold claim. He recognized that feeding carries emotional meaning beyond nutrition, an idea later developed far more rigorously in attachment research.
Overviews of child development theories show how this emphasis on early experience echoes through frameworks that rejected his psychosexual model entirely. And research on oral fixation itself shows something worth remembering for any theory: a description can be accurate even when the explanation behind it is wrong.
Conclusion
The oral stage gave psychology two memorable personality sketches, the dependent optimist and the biting pessimist, along with a confusing pile of labels for them. Research suggests the sketches capture something real, while the weaning story behind them does not. Once this stage wraps up, Freud’s attention turns to toilet training and the struggle for control in the anal stage.
References
- Abraham, K. (1927). A short study of the development of the libido, viewed in the light of mental disorders. In Selected papers of Karl Abraham (D. Bryan & A. Strachey, Trans.). Hogarth Press. (Original work published 1924)
- Ainsworth, M. D. S., Blehar, M. C., Waters, E., & Wall, S. (1978). Patterns of attachment: A psychological study of the Strange Situation. Lawrence Erlbaum.
- Bornstein, R. F. (1992). The dependent personality: Developmental, social, and clinical perspectives. Psychological Bulletin, 112(1), 3-23.
- Bowlby, J. (1969). Attachment and loss: Vol. 1. Attachment. Basic Books.
- Freud, S. (1905). Three essays on the theory of sexuality. In J. Strachey (Ed. & Trans.), The standard edition of the complete psychological works of Sigmund Freud (Vol. 7, pp. 125-243). Hogarth Press.
- Freud, S. (1917). Introductory lectures on psycho-analysis. In J. Strachey (Ed. & Trans.), The standard edition of the complete psychological works of Sigmund Freud (Vols. 15-16). Hogarth Press.
- Kline, P., & Storey, R. (1977). A factor analytic study of the oral character. British Journal of Social and Clinical Psychology, 16(4), 317-328.
- Kline, P., & Storey, R. (1980). The etiology of the oral character. The Journal of Genetic Psychology, 136(1), 85-94.
How to cite this article:
The Psychology Notes Headquarters. (2026). Freud’s Oral Stage: Oral Receptive vs Oral Aggressive Types. Retrieved from https://www.psychologynoteshq.com/freud-oral-stage/